
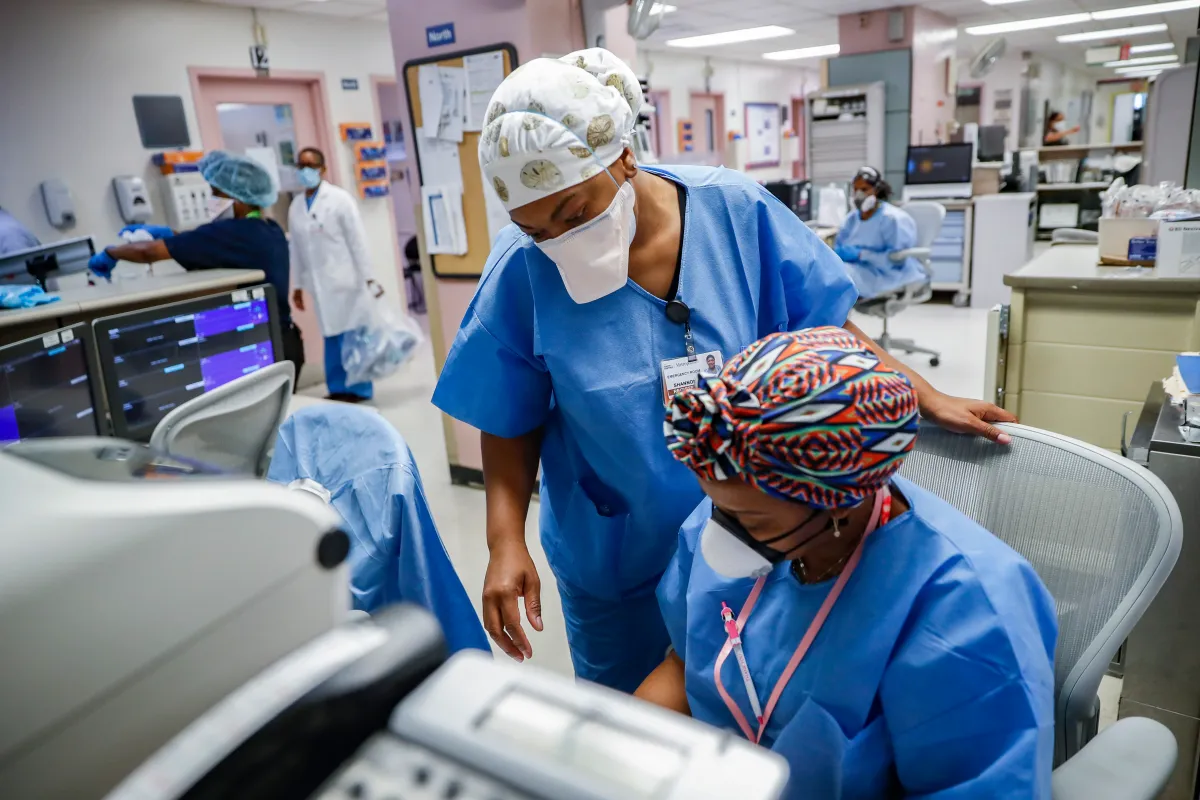
Imagine a system where the emergency department is no longer a crowded waiting room, but a dynamic triage hub, one that routes patients to the right level of care before they deteriorate. Where the nurse who spots a pattern in a patient’s vitals can act on it immediately, without waiting for three layers of approval. Where a primary care team reaches out to a diabetic patient before a crisis develops, because the system has learned to recognize the warning signs. Where a frail elderly person returns home after surgery, supported by a coordinated network of care, not discharged into a void. Where an informed citizen, equipped with the knowledge and tools to manage their own health, rarely needs that emergency department in the first place.
This is not a fantasy; versions of it exist today, in pockets, in fragments, in the work of individuals and teams who refused to accept that the current state was the only possible one. The question this series has been building toward is not whether such a system is conceivable. It is: What will it take to make it the norm rather than the exception?
Over the first three articles, we established a framework. Health care behaves not like a machine but like a complex adaptive system—one that drifts toward fragility when it is over-controlled and over-standardized. We described how self-organized criticality explains why systems that appear stable can collapse suddenly, and why architecture matters as much as resources. We argued that value-based care is not a payment reform, but an operating system. It’s the incentive engine that aligns millions of decisions around a common objective: better outcomes across the full trajectory of care.
All of that is necessary. None of it is sufficient. Because in the end, systems do not transform themselves. People do.
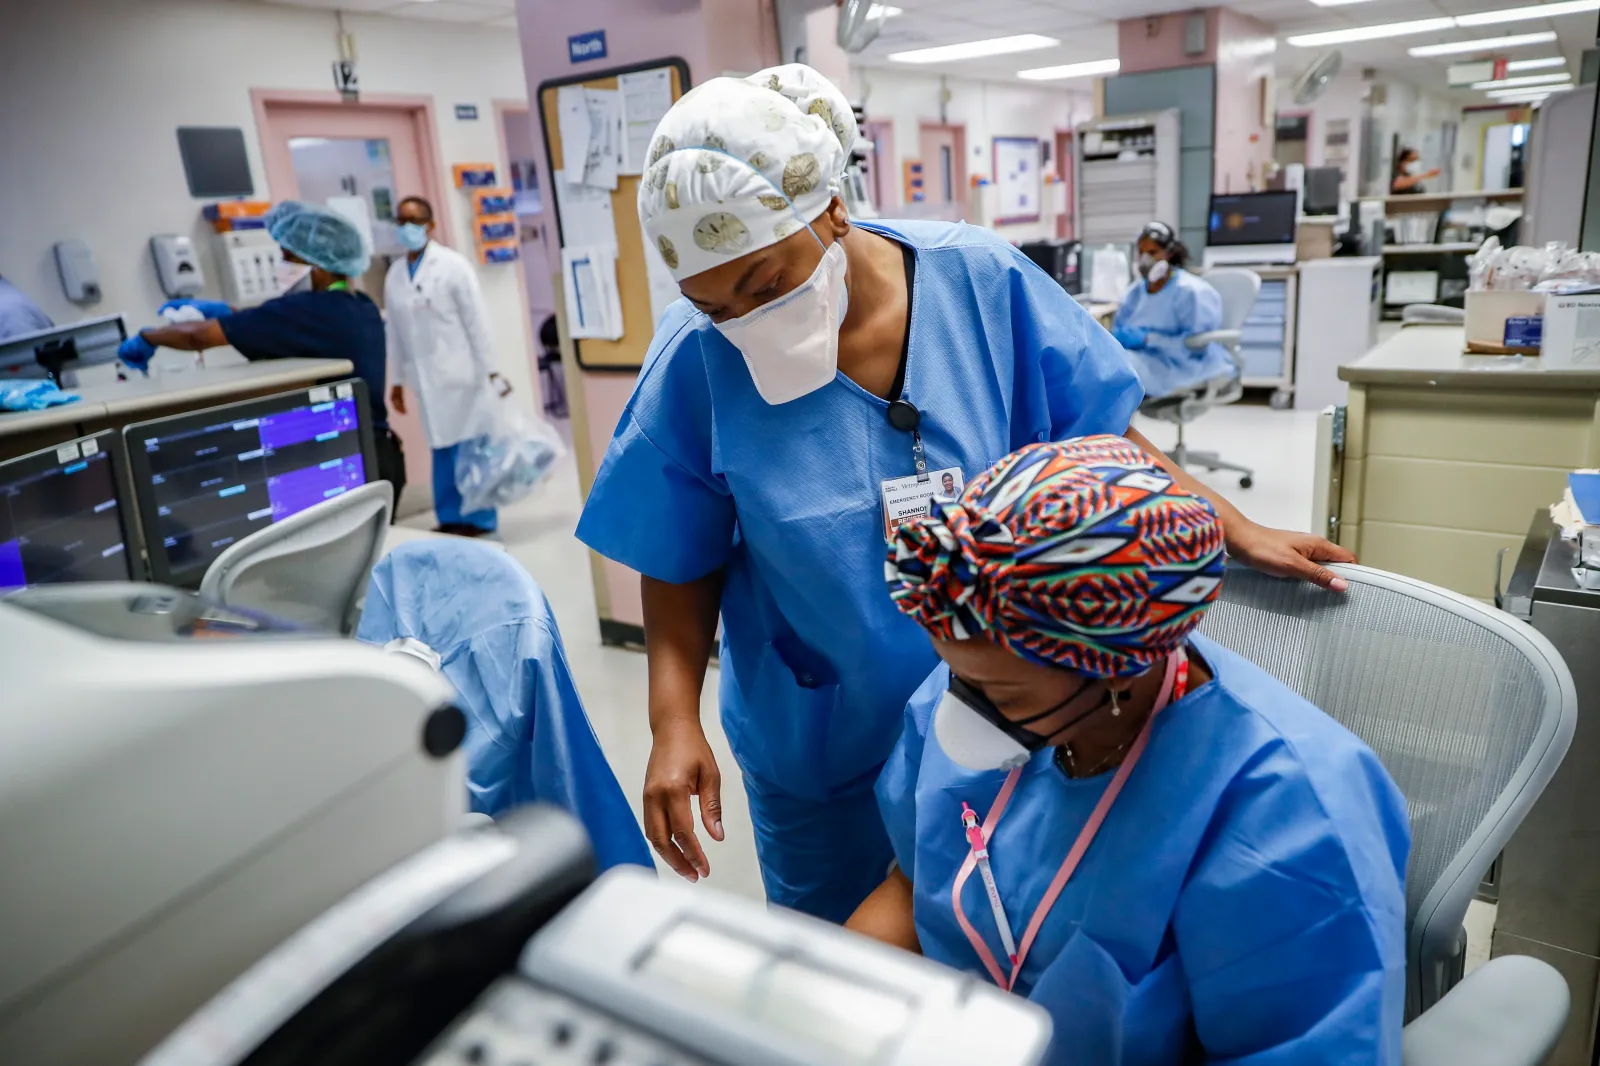
What does that mean in practice? It means three concrete things, each requiring a different kind of courage. For clinicians, it means reclaiming professional agency. The most powerful lever in any health care system is the judgment of the person at the bedside. Decades of protocol-driven medicine, defensive practice and administrative burden have slowly eroded that judgment—not by removing it, but by burying it. Clinicians who practice in outcome-oriented environments describe something qualitatively different: a return to purpose. They are no longer rewarded for doing more. They are rewarded for doing what works. This changes not just behavior, but identity. It restores the reason most people entered medicine in the first place. Practically, it means engaging with outcome data—not as a performance metric imposed from above, but as a mirror that shows whether your patients are genuinely getting better. It means being willing to ask and to answer honestly: What does my practice look like across the full trajectory of care, not just within the encounter I control?
For individual citizens, it means accepting a more demanding—and more empowering—role than the health care system has traditionally asked of them. This is the most underappreciated lever in all of health care transformation, and the most consequential. Chronic disease, which now dominates the global burden of illness, is not primarily managed in clinics. It is managed in kitchens, in bedrooms and in the daily accumulation of small decisions that no clinician can make on a patient’s behalf. The system can treat the consequences of those decisions; it cannot substitute for them.
This requires a fundamental shift in how we think about the relationship between individuals and the systems that serve them. For too long, health care has positioned citizens as recipients—people to whom care is delivered, rather than people who are active architects of their own health. That model was always incomplete. In an era of chronic disease, aging populations and resource-constrained systems, it is no longer viable. Personal responsibility is not a burden to be imposed; it is a capacity to be cultivated. And cultivating it requires one thing above all: education.
Not education in the narrow sense of handing patients a pamphlet at discharge. Education as a continuous, lifelong process in which individuals build genuine health literacy, understand how their choices shape their trajectories and develop the ability to navigate a complex system with confidence rather than confusion. The most resilient health systems of the future will not just treat illness. They will produce informed people who understand their own biology, engage actively with their care teams and take seriously the daily decisions that determine whether they thrive or deteriorate. In this sense, the boundary between the health care system and the individual begins to dissolve. The system becomes, in the most meaningful way, the person.
For leaders and policymakers, it means making decisions that are politically difficult precisely because they are correct. Value-based care threatens entrenched interests. Fee-for-service is not just a payment model; it is an ecosystem with stakeholders who benefit from its continuation. Shifting toward outcome accountability requires the courage to measure things that were previously unmeasured, to make performance visible and to hold institutions—including your own—accountable for results rather than activity. It means investing in primary care and prevention even when hospitals generate more political visibility. It means funding what works over the long term, even when short-term pressures demand something more visible, more announceable and less important.

And running through all of this is equity. A system redesigned around outcomes must confront a hard truth: Outcomes are not equally distributed and they will not become so without deliberate effort. Antifragile health care is not just health care that improves under stress; it is health care that improves for everyone. Equity is not an add-on to systems transformation; it is the test of whether the transformation is real.
What all of these points toward is something more ambitious than a better health care system; it points toward a fundamentally different relationship between people and health itself. For most of its history, health care has been activated by illness—a system that waits, then responds. The shift we are describing moves the intervention point upstream, from treatment to prevention, from crisis to continuity, from episodic contact to ambient presence. Imagine a system that does not wait to be needed; one that surrounds people in their daily lives, continuously monitoring, learning and adjusting; that detects deterioration before it becomes disease; that supports healthy choices in the moments when they are actually made, not in a clinic appointment weeks later.
This is the concept of the ambient health system—not a technology proposition, but an architectural one. It requires the distributed intelligence, the outcome orientation and the educated, empowered citizenry for which this entire series has been arguing. And it reframes the ultimate aspiration: not health care that is more efficient, but health that is more present. Not a system that people enter when something goes wrong, but one that is woven into the fabric of everyday life until, in the most meaningful sense, the system and the person become one.
What makes this moment different from previous reform cycles is that the tools now exist. Outcome measurement has matured; digital infrastructure can support longitudinal tracking in ways that were not possible a decade ago. Artificial intelligence is beginning to make the ambient health system a practical reality by enabling continuous monitoring, early detection of deterioration and personalized learning at a scale no human workforce could sustain alone. The evidence base for value-based models is no longer theoretical; it is growing across multiple health systems and national contexts. The conceptual case has been made. The practical proof points are accumulating. What remains is the harder work: translating understanding into action, at scale, across the millions of daily decisions that constitute a health system.
That work does not begin in a policy document or a boardroom; it begins in a conversation between a clinician and a patient or when a leader chooses to protect an investment in prevention even when something more visible competes for the same budget. But it also requires something that is harder to achieve: the right people at the right policy tables. The expertise needed to navigate what is coming—rooted in complexity science, systems thinking, behavioral economics and the lived realities of care delivery—is different in kind from the expertise that currently dominates most health care policy environments. That gap is not a personal failing; it is a systems problem. And like all systems problems, it requires a deliberate structural solution: bringing new voices, new disciplines and new mental models into the rooms where decisions are made. It begins, in short, whenever someone decides that the way things are is not the way they have to be.
Emergency rooms are still overflowing, clinicians are still burning out and patients are still waiting. We began this series with those facts, because they are true—and because they are not inevitable. The science of complex systems tells us that health care does not fail because the people in it are inadequate. It fails because the system was built for a different purpose than the one we now need it to serve. Rebuilding it will not happen all at once, and it will not be painless. But it will happen—because enough people in enough places are already refusing to accept the alternative. Share this series with someone who needs to hear it; the conversation it starts may be the one that matters most.