
The latest science suggests knees are more resilient than you think.

October 12, 2026 at 6:00 a.m. EDTToday at 6:00 a.m. EDT
Our knees are hinge joints, moving back and forth in a single plane. They support our body weight. They’re central to movement. Want to go for a walk, take the stairs, play sports, lift the kids, exit the car, age gracefully or rise easily from your desk after reading (or writing) this sentence? You’ll need healthy knees.
Our futures hinge on those hinge joints.
But knees are often misunderstood. “People have strong opinions” about what makes and keeps knees healthy, said Jean-Francois Esculier, a physical therapist and clinical associate professor of medicine at the University of British Columbia in Kelowna who studies and treats sports injuries.
In a 2022 study of 2,514 adults led by Esculier, for instance, more than half said they thought distance running increases the risk of knee arthritis. But study after study shows runners generally are less likely than other people to develop painful knee arthritis, and their arthritis usually progresses more slowly if they develop it. Running may even help to strengthen knee cartilage.
The latest science in fact suggests knees can be more resilient than many researchers, clinicians and knee owners once thought. With luck and preparation, our knees may stay in good shape through a full lifetime.
But knees will alter as we age. Some of the changes seem inevitable. Others could be malleable, meaning we have some control over our knees’ futures.
What follows is a science-based guide to your knees during adulthood: how they work and transform with age and tips on how best to protect them.
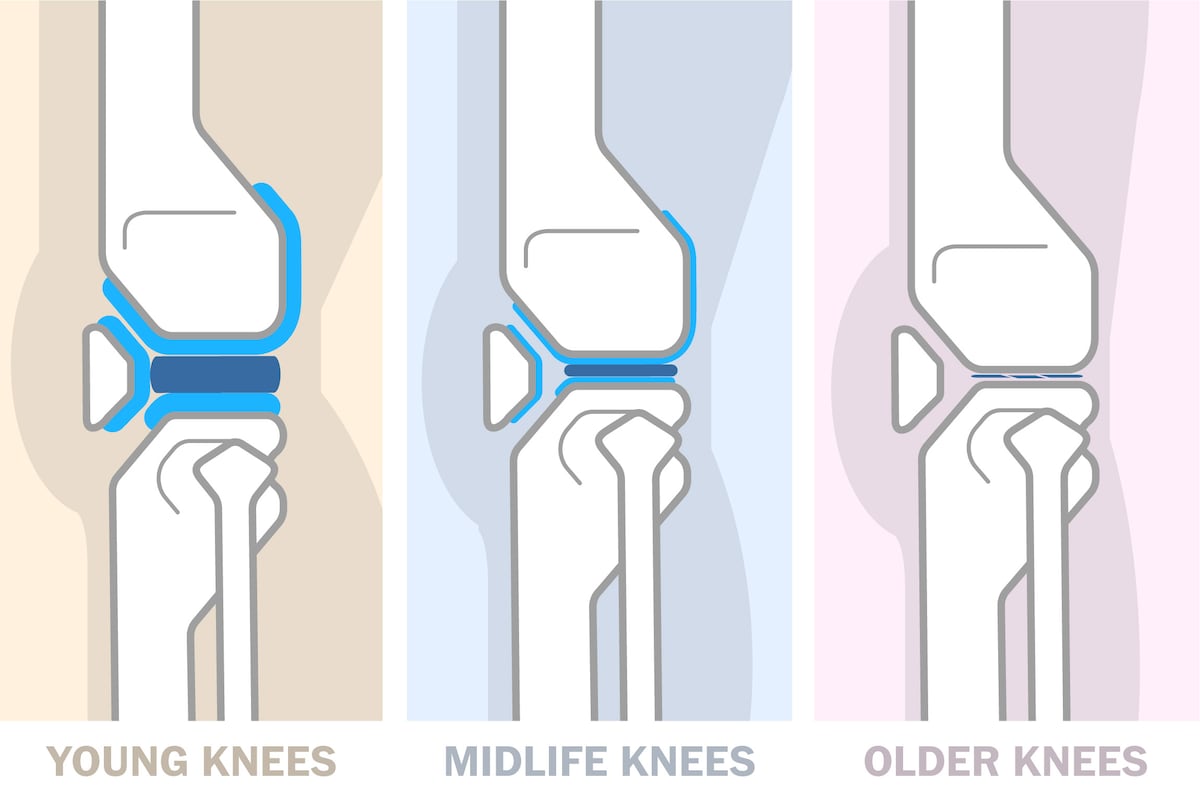
Young knees
20s through 30s
Midlife knees
40s through 50s
Older knees
60s and beyond
Anterior
cruciate
ligament
(ACL)
Anterior
cruciate
ligament
(ACL)
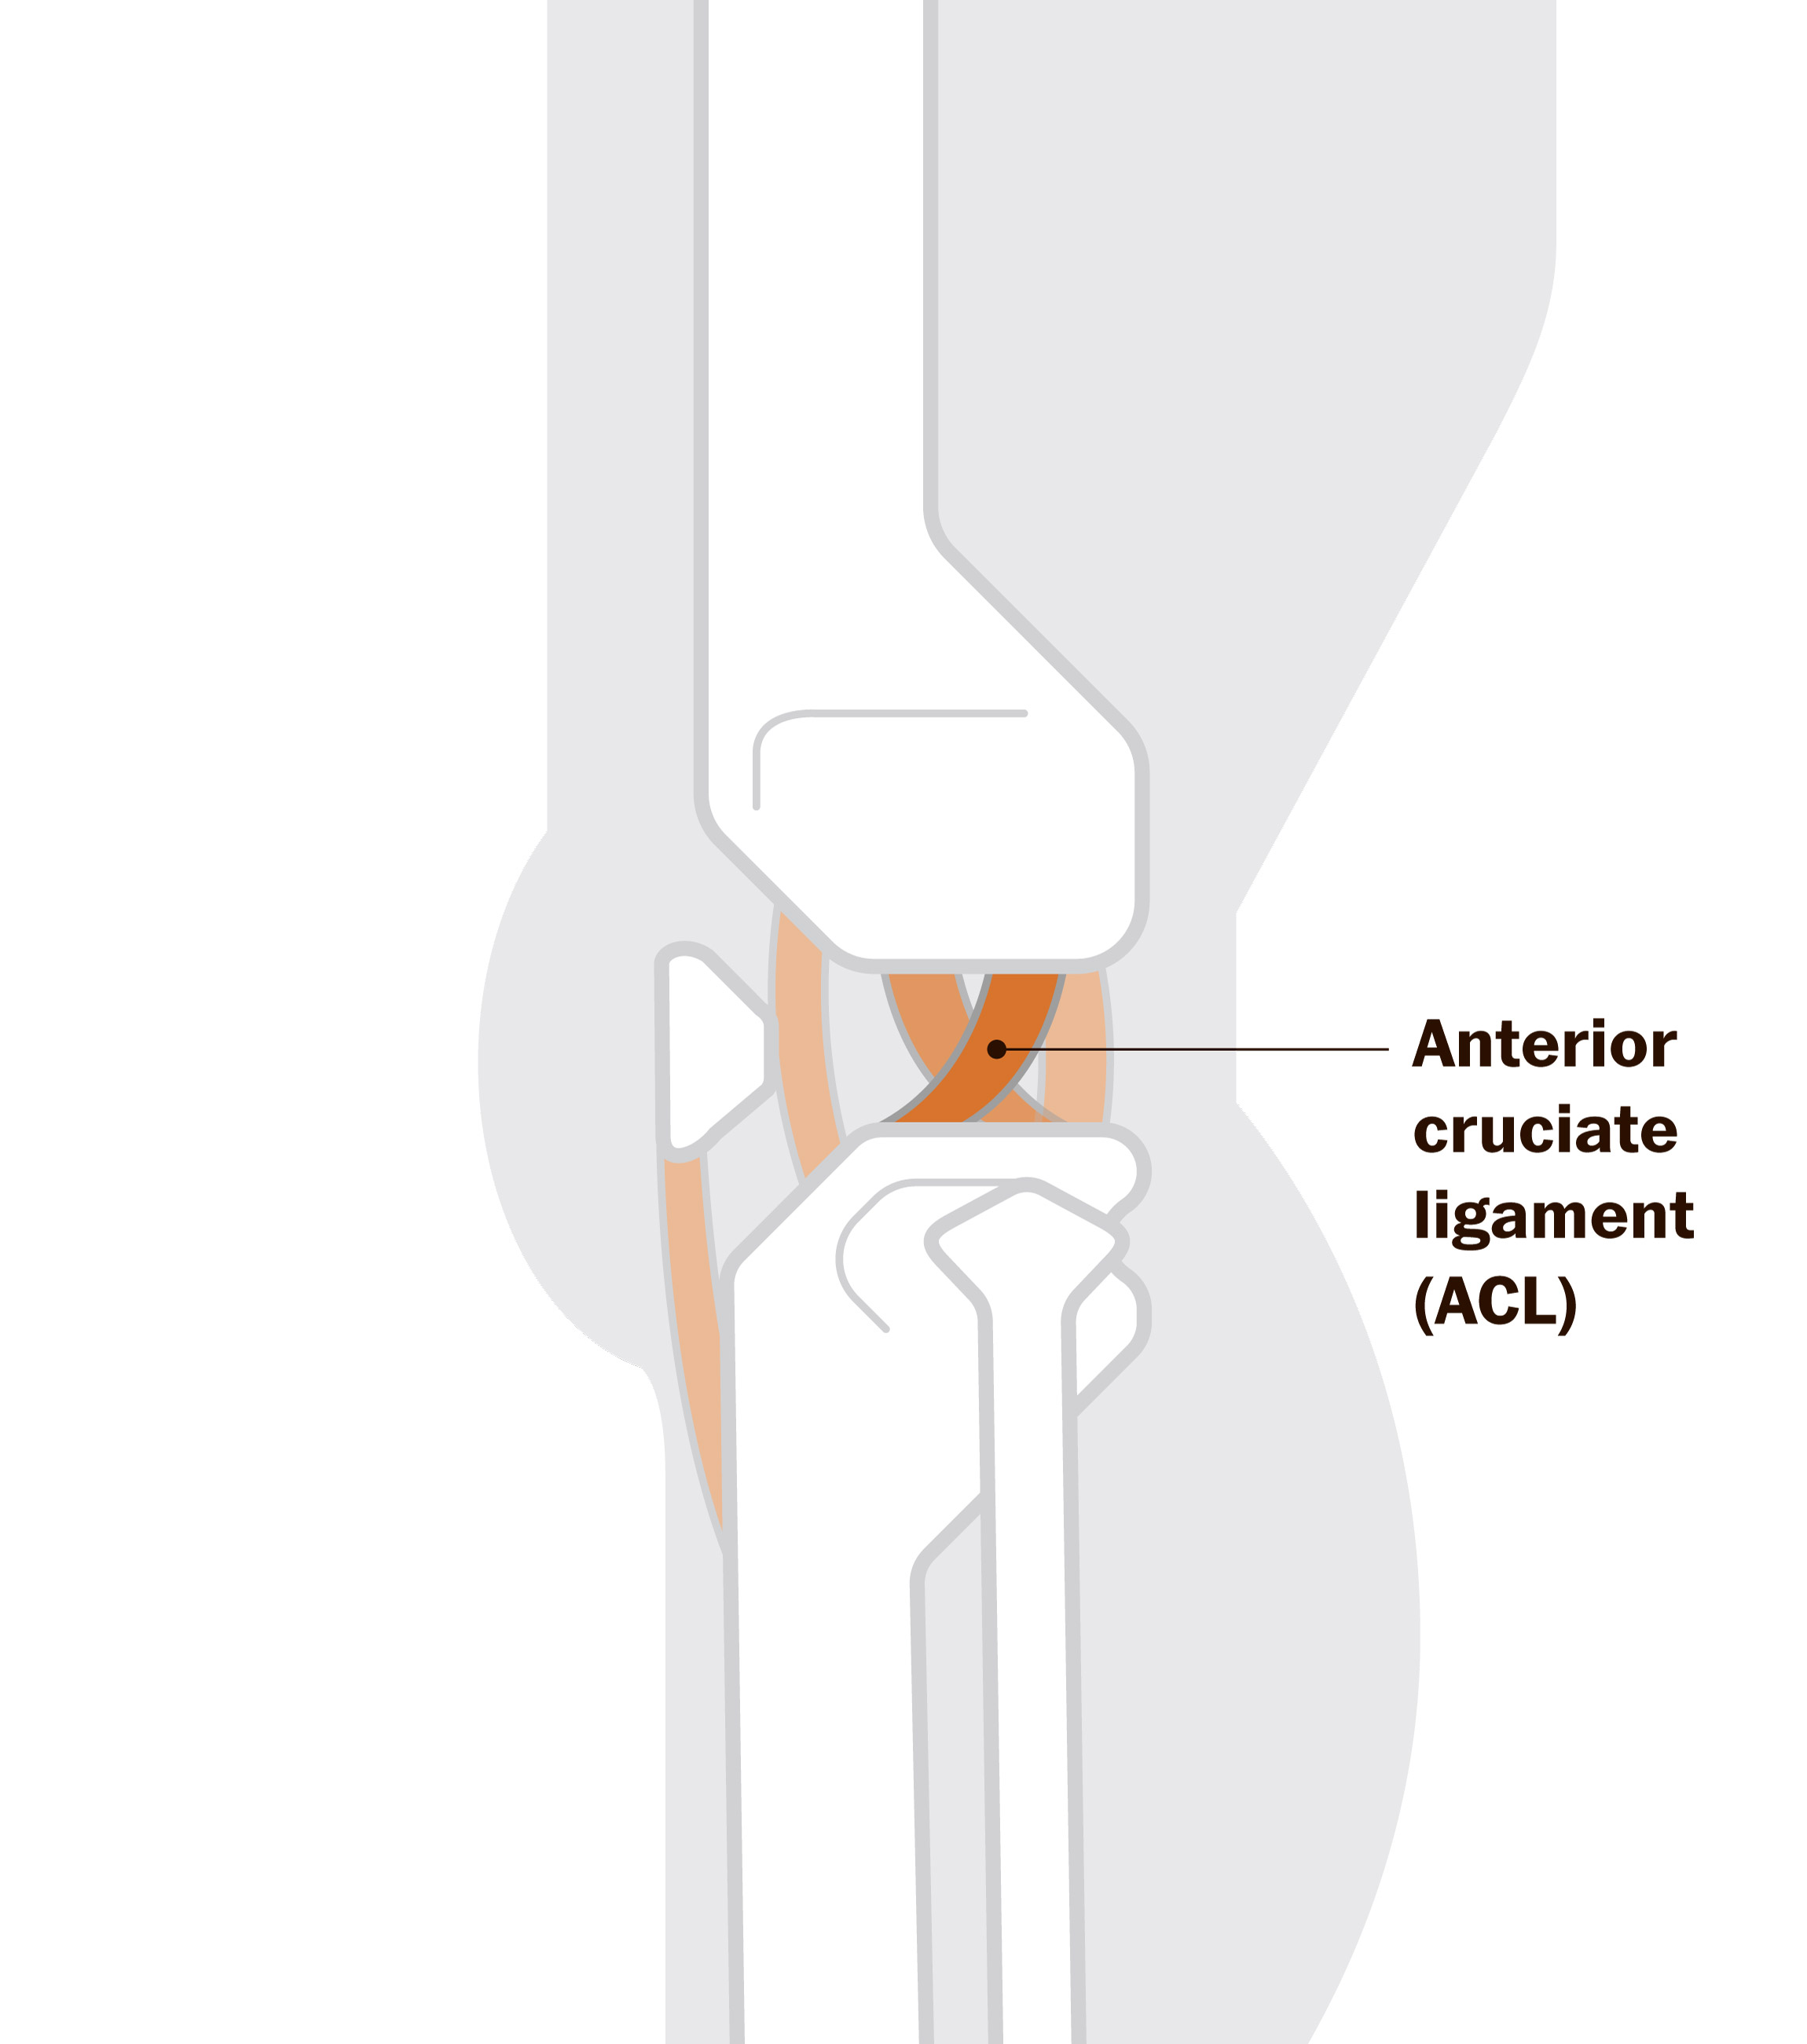
Three intersecting bones — the femur (thighbone), tibia (shinbone) and patella (kneecap) — form the knee, their ends sheathed with thin layers of protective articular cartilage.
The anterior cruciate ligament (ACL) — famous for interrupting or ending athletic careers when torn — connects those bones.
Two thicker cartilage crescents — the menisci — cushion the space between the femur and tibia.
A clear, gooey liquid, called synovial fluid, lubricates the entire joint.
Three large muscle groups connect to and stabilize the knee.
Young knees
At this age, knees demand little care or attention. The joints’ cartilage tends to be at its thickest and healthiest, the bones strong, tendons mostly intact.
Not coincidentally, these are the decades when adults are the most physically active (though lifetime physical activity levels probably peak for most of us at about age 3, research shows, and decline from then on).
This activity is “the key” to healthy joints, including in early adulthood, said Keith Baar, an exercise scientist at McMaster University in Canada who studies musculoskeletal longevity.
When we walk or otherwise move, our knees bend and the joints’ bones compress cartilage, which deflates, releasing fluid. The cartilage then re-plumps — drawing in fluid filled with oxygen and nutrients — as knees straighten, a process called cyclic loading, which helps nourish and replenish the cartilage.
Activity is at the heart of cyclic loading. In a 2024 study, if young adults stood quietly for 30 minutes, their knees’ cartilage stayed almost flattened throughout. If they lay down for 50 minutes, the cartilage began to recover. But if they walked for 10 minutes, their knees’ cartilage fully reinflated three times faster than at rest.
Young knees do face challenges. Muscle mass and strength begin declining around age 30, especially in the large leg muscles that help stabilize the knee. Knees may feel no different as muscles shrink but become more susceptible to injury or osteoarthritis.
Sports injuries now also predispose knees to problems later. The incidence of ACL tears peaks by about age 25 in men and 18 in women, with long-term repercussions. By some estimates, nearly half of young people who tear an ACL develop signs of early arthritis within a decade.
Midlife knees
Knees may start to trouble us now. The typical age for a diagnosis of knee arthritis is about 55, with rising numbers among 40-year-olds.
Even without arthritis, studies show knees can change in worrying ways during midlife.
Synovial fluid may begin drying up and losing viscosity.
Declines in leg strength, power and muscle mass accelerate. Sedentary middle-aged men and women lose about 10 percent of their strength and mass each decade, weakening knees, too.
Cartilage often thins and frays. In a 2018 study, knee scans showed articular cartilage tears in nearly half of a group of adults aged 40 or older, many of whom hadn’t reported knee pain. Almost 20 percent separately or in addition had a meniscus tear.
Weight may increase. By some estimates, most men and women gain almost a pound a year throughout midlife. This can amplify loads on the knee and raise bodily inflammation, which is believed to damage the knee and contribute to arthritis risk.
Many of us become more sedentary. Daily step counts in midlife often hover at or below 5,500 per day. Less movement means less cyclic loading, affecting cartilage health.
The good news: Continuing or increasing exercise during midlife protects knees, especially weight training. A 2024 study of 2,607 men and women found that resistance exercise before age 50 dropped the risks of later knee pain or arthritis by 20 percent or more.
Regular walking in midlife is also beneficial for knees.
Even distance running may help. In a 2019 study, 82 middle-aged men and women had knee scans before training for their first marathon. The scans revealed widespread cartilage, tendon and other damage, though no one reported knee pain. After six months of training for and completing the London Marathon, subsequent scans showed the runners’ knees looked healthier than before, with less cartilage or other damage.
Older knees
These are the decades of our knees’ discontent. Of the nearly 800,000 knee replacements in the United States each year, most are among people in their 60s, according to government statistics, with case numbers peaking at about age 66.
Common joint problems usually intensify and compound now. A majority of older people are likely to have at least one meniscus tear, for instance, studies show, even if they don’t feel knee pain.
The cartilage between bones often thins more rapidly after age 60, too, leaving the femur and tibia with less cushioning, so the separation between the bones lessens or disappears. This condition is called joint-space narrowing, a hallmark of knee arthritis that can lead to bone-on-bone friction during movement.
In general, older knees also have less lubricating synovial fluid than younger ones and the fluid is more watery and carries fewer nutrients.
Muscle and strength loss speed up now, with the declines disproportionately striking the big quadriceps muscles in our thighs, key knee stabilizers.
But almost none of these effects are inevitable with aging, researchers say. Many can be reduced or avoided, especially with activity.
Simply walking a little more improves the health and function of most older knees. In one study, older people with or at risk of knee arthritis who took at least 6,000 steps a day maintained their mobility and felt less pain than those who didn’t. Even if people took fewer than 6,000 steps, knee function improved by about 16 percent for every additional 1,000 steps a day they managed.
Squats work, too, focusing, as they do, on the quadriceps. After 16 older men and women began a 12-week program of chair squatting for a 2021 study in Scientific Reports, their quads’ size and strength grew and they were able to rise more rapidly from chairs, a marker of functional strength that relies, fundamentally, on having good knees.
This story is the first in a week-long series about knee health. Tomorrow, hear from a knee doctor about the worst thing you can do for sore knees.
About this story
Development by Junne Joaquin Alcantara. Story editing by Emily Codik and Theresa Tamkins. Graphics editing by Emily M. Eng. Copy editing by Karl Hente.