
Following up on our previous post, we are continuing to sequence Bundibugyo virus (BDBV) genomes and performing phylodynamic analyses to understand how the current outbreak started and is unfolding.
Laboratory diagnosis of Bundibugyo virus disease (BVD) and wet lab sequencing were performed as specified in previous posts: Genomic epidemiology of the ongoing 2026 Bundibugyo Virus Disease outbreak in the Democratic Republic of the Congo. Briefly, clinical specimens included EDTA whole-blood samples from living patients and oral fluid specimens from deceased patients were collected from suspected cases of BVD in the Democratic Republic of the Congo (DRC). Specimens were analyzed at either (1) the Institut National de Recherche Biomédicale (INRB), Kinshasa, (2) the Laboratoire Provincial de Santé Publique (LPSP, Provincial Public Health Laboratory), Ituri or (3) Decentralized laboratories located within Ebola treatment centers in Ituri province using the RADIONE Point-of-care system (KH Medical, Pyeongtaek-si, South Korea) and the RealStar Filovirus Screen RT-PCR kit 1.0 or 2.0 (Altona Diagnostics, Hamburg, Germany). We subsequently sequenced all PCR-positive samples with Cycle threshold (Ct) values <31.
We used the amplicon-nf v.2 https://artic.network/resources/amplicon-nf pipeline for consensus generation.
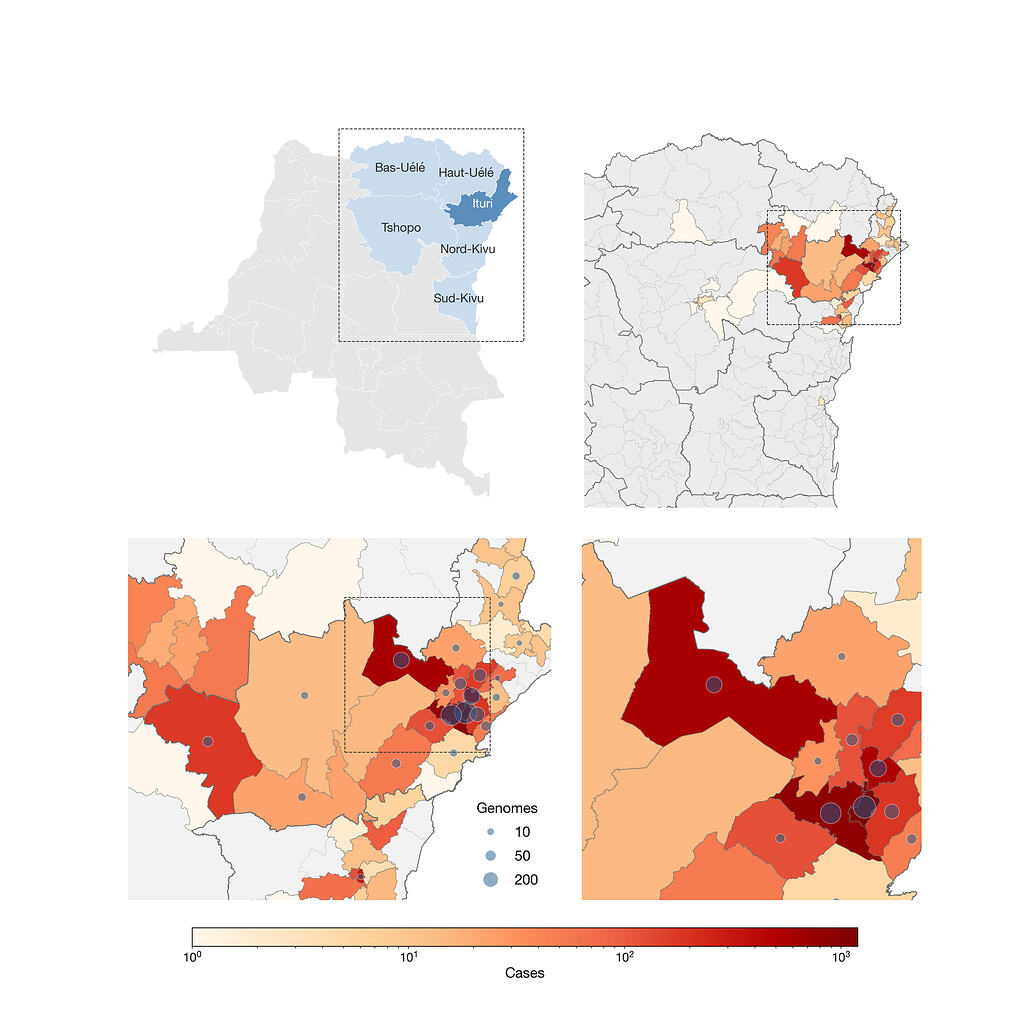
A total of 626 genomes from 21 Health Zones in Ituri (n=625) and 1 Health Zone in Nord-Kivu (n=1) Provinces (Figure 1) were sequenced and have been deposited on pathoplexus.org. Sampling dates span between 02-May-2026 and 9-Aug-2026. These can be accessed as Pathoplexus SeqSet BDBV_DRC_20260820 [PP_SS_3400.1 | Pathoplexus].
Figure 1 | Provinces (upper left) and Health Zones (upper right) with confirmed cases. Location of sampling of the 626 genomes described here (bottom left), with outlined area zoomed in further to the Health Zones with the most cases and genomes (bottom right). All but one genome are from Health Zones in Ituri Province with the remaining one from Katwa in Nord-Kivu.
626 genomes Pathoplexus SeqSet BDBV_DRC_20260820 from DRC sampled between 2026-05-02 and 2026-08-09.
32 genomes were removed because they showed evidence of ADAR editing (Table 1).
Aligned using MAFFT (Katoh et al, 2002) – resulting alignment contained no indels.
The alignment was trimmed to length 18,900 to remove sequencing artefacts at the end of the genome (one genome exhibited these: 26FHV054, PP_006XHL9.3).
Maximum likelihood tree using IQ-TREE 3 (Wong et al 2025) (ModelFinder (Kalyaanamoorthy et al, 2017) selected the GTR+F+R3 substitution model) and with small branch lengths collapsed to zero.
The phylogenetic tree was rooted to minimise residuals from the regression line. We identified genomes noticeably outside ±2 standard deviations of the residuals, removed the genomes, rerooted the tree to minimise residuals, and performed this series of steps a second time to remove one additional set of outliers, resulting in the cumulative removal of 69 genomes (Table 1).
To infer the timescale and basic epidemiological characteristics of the data set we used BEAST X v10.6.0-beta2 (Baele et al 2025). Two coalescent-based tree prior models were employed: exponential growth and the SkyGrid non-parametric model (Gill et al, 2013) with 31 transition points at one week intervals and a cutoff of 32 weeks. A GTR model was employed with default priors and transition kernels. Runs were 100m steps, with 10,000 samples taken with a 10% burnin.
The maximum likelihood tree (Figure 2) exhibits a good temporal signal (Figure 3), with a regression slope of 7.9E-4. Our results indicate increased phylogenetic diversity relative to our previous analysis of 139 genomes [Genomic epidemiology of the ongoing 2026 Bundibugyo Virus Disease outbreak in the Democratic Republic of the Congo], Our initial analysis included 96 genomes from Bunia and Rwampara and 9 from Mongbwalu, whereas we now include 308 from Bunia and Rwampara and 47 from Mongbwalu (Figure 2).
We inferred an evolutionary rate of 8.5E-4 substitutions per site per year (95% highest posterior density interval [HPDI]: 7.3–9.8E-4) under the SkyGrid coalescent model, with a time of the most recent common ancestor (tMRCA) of 22 February 2026 (95% HPDI: 16 January 2026 – 24 March 2026). Under this model (considering 32 one-week intervals) the epidemic shows exponential growth over this time period but with a time-varying rate, indicating a relatively slow start and then an increased rate of growth from March until June, after which the rate appears to decline (Figure 4).
Assuming that exponential growth is constant from the tMRCA to the most recently sampled tip (9 August), the estimated doubling time is 21.0 days (95% HPDI: 15.0 – 40.7) and the tMRCA estimate is pushed back to 21 January 2026 (95% HPDI: 14 December 2025 – 20 February 2026). Note that the inferred rate of evolution is approximately the same under both models.
Genomes from Mongbwalu appear to represent substantial diversity in the maximum likelihood phylogeny, as well as emerging from relatively deep parts of both the maximum likelihood and time-calibrated phylogenies (Figures 2, 5). The root age and Skygrid reconstruction are compatible with a slow start of the epidemic in Mongbwalu, followed by exportations and an increased growth rate as larger urban areas (e.g., Bunia) were seeded. These results would be concordant with epidemiological reports suggesting that Mongbwalu could have been a starting point for the outbreak (WHO, 2026). Additionally, we find that genomic and phylogenetic diversity was maintained and increasing during the sampling period, without any indication of fitness-altering mutations or a particular lineage starting to dominate.
We note there are fewer genomes sampled after mid-July (Figure 5), and these results should be understood as preliminary and taken with caution.
Figure 2 | Maximum likelihood tree with tips colored by Health Zone of sampling. Genomes from the DRC but not from Bunia, Rwampara, or Mongbwalu are grouped together into a single category. Show in PearTree.
Figure 3 | Root-to-tip plot of 525 genomes after removing 32 genomes with signatures of ADAR-editing and 69 genomes identified as outliers. The estimated rate of evolution is 7.9E-4 and a tMRCA of early February 2025, compatible with estimates from BEAST. The color scheme matches that of Figure 2.
Figure 4 | A. Skygrid reconstruction of relative population size over time. The blue line shows the mean estimate, and the shaded region represents the 95% HPD interval. The heavy dashed line indicates the median tMRCA (22 February 2026), while the dotted line indicates the upper bound of the 95% HPD interval (24 March 2026); the lower bound (16 January 2026) coincides with the lower limit of the y-axis. The exponential growth reconstruction is shown in orange. A rug plot at the bottom of the panel shows the dates and frequency of genomes included in the analysis. B. Daily case counts (RT-qPCR positive) by symptom onset in Mongbwalu (red), Bunia and Rwamparu (green), the rest of Ituri (gold), and the rest of the DRC (grey).
Figure 5 | Time-calibrated summary tree from the Skygrid analysis. The tMRCA is represented by a violin at the root, with the median indicated by a vertical green line, the 95% HPD by the larger grey violin, and the 50% HPD by the inner green violin. Open in PearTree.
Key contributors to data collection/molecular testing/data interpretation/whole genome sequencing/bioinformatics analysis/phylogenetic analysis, and manuscript writing:
Institut National de Recherche Biomédicale (INRB), Kinshasa – DRC and partners
Adrienne Amuri-Aziza (INRB, Kinshasa, DRC)
Prince Akil-Bandali (INRB, Kinshasa, DRC)
Jonathan E. Pekar (University of Edinburgh, UK)
Pascal Adroba Tandele (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Eddy Kinganda-Lusamaki (INRB, University of Kinshasa, Kinshasa, DRC; TransVIHMI, Université de Montpellier, INSERM, IRD, Montpellier, France)
Moritz U.G. Kraemer (University of Oxford, UK)
Olga Ntumba-Tshitenge (World Health Organization Country Office, Kinshasa, DRC)
John O. Otshudiema (World Health Organization Regional Office for Africa, Brazzaville, Republic of Congo)
Amadou Mouctar Diallo (World Health Organization Country Office, Kinshasa, DRC)
Princesse Paku-Tshambu (INRB, Kinshasa, DRC)
Phine Malengo-Olokakoy (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Rilia Ola-Mpumbe (INRB, Kinshasa, DRC)
Neema Kavugho-Sindani (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Ange Ponga-Museme (INRB, Kinshasa, DRC)
Gradi Luakanda-Ndelemo (INRB, Kinshasa, DRC)
Emmanuel Lokilo-Lofiko (INRB, Kinshasa, DRC)
Daan Jansen (Institute of Tropical Medicine, Antwerp, Belgium)
Lievin Tibasima-Dhesa (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Marcel Lola-Loway (Division Provinciale de la Santé, Ituri, DRC)
Benjamin Djemba-Fundji (Laboratoire Provincial de Santé Publique, Ituri, DRC)
François Berocan-Underos (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Berkias Bakambu-Nebape (Laboratoire Provincial de Santé Publique, Ituri, DRC)
Fiston Cikaya-Kankolongo (INRB, Kinshasa, DRC)
Judith Tete-Sitra (INRB, Kinshasa, DRC)
Pauline-Chloé Muswamba-Kayembe (INRB, Kinshasa, DRC)
Raphael Lumembe – Numbi (INRB, University of Kinshasa, Kinshasa, DRC)
Julie Tuenakoko-Kulumbula (INRB, Kinshasa, DRC)
Nelson Kashali (INRB, Kinshasa, DRC)
David Isengelo-Sikatenda (INRB, Kinshasa, DRC)
LeBon Matendo-Kakina (INRB, Kinshasa, DRC)
Jean-Claude Makangara-Cigolo (INRB, University of Kinshasa, Kinshasa, DRC; Institute of Social and Preventive Medicine, University of Bern, Bern, Switzerland)
Servet Kimbonza (INRB, Kinshasa, DRC)
Elzedek Mabika-Bope (INRB, Kinshasa, DRC)
Patrick Mukadi-Kakoni (INRB, University of Kinshasa)
Daniel Mukadi-Bamuleka (INRB, University of Kinshasa, Laboratoires P2/P3, Rodolphe-Merieux INRB-Goma, DRC)
Dav Ebengo (INRB, INOHA, DRC)
Nick Loman (University of Birmingham, UK)
Sam Wilkinson (University of Birmingham, UK)
Josh Quick (University of Birmingham, UK)
Chris Kent (University of Birmingham, UK)
Sam Richardson (University of Birmingham, UK)
Charlotte Pratt (University of Birmingham, UK)
Bernardo Gutierrez (University of Oxford, UK)
Renny Doig (Simon Fraser University, Canada)
Ciara Judge (University of Oxford)
Joseph L.-H. Tsui (University of Oxford)
Caroline Colijn (Simon Fraser University, Canada)
Emma Hodcroft (University of Basel, Switzerland)
Martine Peeters (TransVIHMI, Université de Montpellier, INSERM, IRD, Montpellier, France)
Ahidjo Ayouba (TransVIHMI, Université de Montpellier, INSERM, IRD, Montpellier, France)
Eric Delaporte (TransVIHMI, Université de Montpellier, INSERM, IRD, Montpellier, France)
Collins Kipngetich Tanui (Africa CDC)
Justus Nsio (Africa Centres for Disease Control and Prevention, Addis Ababa, Ethiopia)
Marie-Roseline Belizaire (World Health Organization Regional Office for Africa, Brazzaville, Republic of Congo)
Kevin K. Ariën (Institute of Tropical Medicine, Antwerp, Belgium)
Laurens Liesenborghs (Institute of Tropical Medicine, Antwerp; KU Leuven, Leuven, Belgium)
Guy Baele (KU Leuven, Leuven, Belgium)
Áine O’Toole (University of Edinburgh, UK)
Christian Happi (African Center of Excellence for Genomics of Infectious Diseases, Redeemer’s University, Ede, Nigeria)
Anne Rimoin (Department of Epidemiology, Jonathan and Karin Fielding School of Public Health, University of California, Los Angeles, CA, USA)
Lisa E. Hensley (US Department of Agriculture, Manhattan, KS, USA)
Sofonias Kifle Tessema (Gates Foundation)
Yenew Kebede (Africa CDC)
Lorenzo Subissi (WHO)
Nicksy Gumede (WHO AFRO)
Christian Ngandu (Institut National de Santé Publique (INSP), Kinshasa, DRC)
Piet Maes (European Plotkin Institute for Vaccinology, Université Libre de Bruxelles (ULB), Brussels, Belgium)
Dieudonné Mwamba (Institut National de Santé Publique (INSP), Kinshasa, DRC)
Pierre Akilimali (Institut National de Santé Publique (INSP), Kinshasa, DRC)
Miles W. Carroll (University of Oxford, Oxford, UK)
Jason Kindrachuk (University of Manitoba, Winnipeg, Manitoba, Canada)
Koen Vercauteren (Institute of Tropical Medicine, Antwerp, Belgium)
Steve Ahuka-Mundeke (INRB, University of Kinshasa, Kinshasa, DRC)
Jean-Jacques Muyembe-Tamfum (INRB, University of Kinshasa, Kinshasa, DRC)
Andrew Rambaut (University of Edinburgh, UK)
Tony Wawina-Bokalanga (INRB, University of Kinshasa, Kinshasa, DRC; Department of Clinical Sciences, Institute of Tropical Medicine, Antwerp, Belgium)
Placide Mbala-Kingebeni (INRB, University of Kinshasa, Kinshasa, DRC; South African National Bioinformatics Institute, University of the Western Cape, South Africa).
We thank the Ministry of Public Health, Hygiene and Social Welfare of the DRC. The authors gratefully acknowledge the ongoing support of the Africa Centers for Disease Control and Prevention (Africa CDC), the World Health Organization, and partner non-governmental organizations. We also acknowledge the support provided by the Unité de Gestion du Programme de Développement du Système de Santé (UG-PDSS), the Institute of Tropical Medicine (ITM) through Belgian Directorate-general for Development Cooperation and Humanitarian Aid (DGD FA5 project, the Culmen International LCC, the US CDC Atlanta, and the Agence Française de Développement through the AFROSCREEN project (grant agreement CZZ3209), coordinated by ANRS Maladies Infectieuses émérgentes in partnership with Institut Pasteur and Institut de Recherche pour le Développement, the French Ministry of Europe and Foreign Affairs through FEF programme and support provided by Institut de Recherche pour le Développement. AREBO project funded by ANRS-MIE. A.A.-A is supported by a DGD sandwich PhD scholarship. N.L., S.W., J.Q., C.K., R.D., C.C., E.H., J.E.P., A.O’T., A.R & P.M-K. acknowledge the support of the Wellcome Trust through the ARTIC Network (award 313694/Z/24/Z) and the Gates Foundation. M.U.G.K. acknowledges funding from The Rockefeller Foundation (PC-2022-POP-005, also A.R.), Health AI Programme from Google.org, the Oxford Martin School Programmes in Pandemic Genomics & Digital Pandemic Preparedness, European Union’s Horizon Europe programme projects MOOD (#874850) and E4Warning (#101086640), Wellcome Trust grants 303666/Z/23/Z, 226052/Z/22/Z & 228186/Z/23/Z, the United Kingdom Research and Innovation (#APP8583), the Medical Research Foundation (MRF-RG-ICCH-2022-100069), UK International Development (301542-403), the Bill & Melinda Gates Foundation grants (INV-063472, INV-090281, INV-103122) and Novo Nordisk Foundation (NNF24OC0094346). The contents of this publication are the sole responsibility of the authors and do not necessarily reflect the views of the European Commission or the other funders. The authors are also grateful for the support of the John D. and Catherine T. MacArthur Foundation, Flu Lab, and a cohort of generous donors through TED’s Audacious Project, including the ELMA Foundation, MacKenzie Scott, the Skoll Foundation, and Open Philanthropy. We also acknowledge Oxford Nanopore Technologies (ONT) for providing sequencing R10 flow cells that partially supported this work.
Statement on continuing work and analyses prior to publication
Please note that this data is based on work in progress and should be considered preliminary. Our analyses are ongoing, and a publication communicating our findings is in preparation. Sequences are publicly accessible under the Pathoplexus ‘Restricted’ licence and we would be grateful if the terms of this were respected. If you intend to use our data prior to our publication, please contact Dr Tony Wawina-Bokalanga (INRB, DRC) and/or Prof. Placide Mbala-Kingebeni (INRB, DRC).
Table 1 | Genomes excluded from phylogenetic analysis and reason for exclusion.
Sample ID
Accession
Reason*
BIA-1299
PP_00764QW
Signatures of ADAR editing
BIA-2971
PP_007AFQB
Signatures of ADAR editing
BIA-3038
PP_007A56Q
Signatures of ADAR editing
BIA-3217
PP_007AF2N
Signatures of ADAR editing
BIA-3599
PP_007AED1
Signatures of ADAR editing
BIA-3664
PP_007AEKN
Signatures of ADAR editing
BIA-3669
PP_007AENG
Signatures of ADAR editing
BIA-4180
PP_007C78E
Signatures of ADAR editing
BIA-4301
PP_007ESCH
Signatures of ADAR editing
BIA-4482
PP_007ESDF
Signatures of ADAR editing
BIA-4581
PP_007ESAM
Signatures of ADAR editing
BIA-4627
PP_007ESBK
Signatures of ADAR editing
BIA-4708
PP_007ESED
Signatures of ADAR editing
BIA-4731
PP_007ES9P
Signatures of ADAR editing
BIA-4768
PP_007ESFB
Signatures of ADAR editing
BIA-4782
PP_007BZQR
Signatures of ADAR editing
BIA-4836
PP_007ES4Z
Signatures of ADAR editing
BIA-4855
PP_007ES5X
Signatures of ADAR editing
BIA-4863
PP_007ES6V
Signatures of ADAR editing
BIA-4864
PP_007ES7T
Signatures of ADAR editing
BIA-4877
PP_007ES8R
Signatures of ADAR editing
BIA-4931
PP_007ESG9
Signatures of ADAR editing
BIA-5188
PP_007ERNX
Signatures of ADAR editing
BIA-5226
PP_007C6F1
Signatures of ADAR editing
BIA-5237
PP_007C4RG
Signatures of ADAR editing
BIA-5245
PP_007C4TC
Signatures of ADAR editing
BIA-5637
PP_007BXK3
Signatures of ADAR editing
BIA-6194
PP_007EXUD
Signatures of ADAR editing
MG-0747
PP_007EWH2
Signatures of ADAR editing
MG-0881
PP_007EYF5
Signatures of ADAR editing
NIZ-141
PP_007C74N
Signatures of ADAR editing
NIZ-37
PP_007C6X2
Signatures of ADAR editing
26FHV0224
PP_0075Z66
Outlier, +ve
26FHV0325
PP_0075ZAY
Outlier, +ve
BIA-1345
PP_00764TQ
Outlier, +ve
BIA-1621
PP_00765FE
Outlier, -ve
BIA-2075
PP_0076518
Outlier, +ve
BIA-2408
PP_007A4G5
Outlier, +ve
BIA-2476
PP_007A4LW
Outlier, +ve
BIA-2576
PP_007A2K0
Outlier, -ve
BIA-2871
PP_007A510
Outlier, -ve
BIA-2883
PP_007A38N
Outlier, +ve
BIA-3476
PP_007A62X
Outlier, +ve
BIA-3668
PP_007AEMJ
Outlier, +ve
BIA-3706
PP_007A6CB
Outlier, -ve
BIA-4155
PP_007C7AA
Outlier, +ve
BIA-4271
PP_007BXZ9
Outlier, -ve
BIA-4293
PP_007BY15
Outlier, +ve
BIA-4304
PP_007BY23
Outlier, -ve
BIA-4310
PP_007BY31
Outlier, -ve
BIA-4312
PP_007BY5X
Outlier, -ve
BIA-4336
PP_007BY6V
Outlier, -ve
BIA-4352
PP_007BY8R
Outlier, -ve
BIA-4382
PP_007C7MM
Outlier, +ve
BIA-4472
PP_007BZ8Q
Outlier, +ve
BIA-4647
PP_007BWNY
Outlier, +ve
BIA-4683
PP_007BYBK
Outlier, -ve
BIA-4709
PP_007BZJ3
Outlier, -ve
BIA-4780
PP_007BZPT
Outlier, -ve
BIA-4879
PP_007BYPU
Outlier, -ve
BIA-4881
PP_007BYTL
Outlier, -ve
BIA-4883
PP_007BYUJ
Outlier, -ve
BIA-4943
PP_007C5W5
Outlier, -ve
BIA-4973
PP_007C61V
Outlier, -ve
BIA-4996
PP_007C66K
Outlier, -ve
BIA-5022
PP_007C68F
Outlier, -ve
BIA-5047
PP_007BYZ8
Outlier, -ve
BIA-5059
PP_007BZ30
Outlier, -ve
BIA-5063
PP_007BZ6U
Outlier, -ve
BIA-5074
PP_007ERSP
Outlier, +ve
BIA-5075
PP_007ERRR
Outlier, +ve
BIA-5093
PP_007C6E3
Outlier, -ve
BIA-5246
PP_007C4UA
Outlier, -ve
BIA-5284
PP_007C76J
Outlier, -ve
BIA-532
PP_0076435
Outlier, +ve
BIA-5376
PP_007BWTN
Outlier, -ve
BIA-5577
PP_007C50Y
Outlier, -ve
BIA-5587
PP_007C51W
Outlier, +ve
BIA-5588
PP_007C52U
Outlier, +ve
BIA-5589
PP_007C53S
Outlier, +ve
BIA-5615
PP_007C57J
Outlier, +ve
BIA-5629
PP_007BXJ5
Outlier, -ve
BIA-5697
PP_007BXRR
Outlier, -ve
BIA-5714
PP_007BXSP
Outlier, -ve
BIA-5722
PP_007BXTM
Outlier, -ve
BIA-5735
PP_007BXUK
Outlier, -ve
BIA-5955
PP_007ERZ9
Outlier, -ve
BIA-6012
PP_007C5HX
Outlier, +ve
BIA-6019
PP_007C5KT
Outlier, -ve
BIA-6363
PP_007ET22
Outlier, +ve
BIA-6448
PP_007ESRQ
Outlier, +ve
BIA-6455
PP_007ESVG
Outlier, +ve
BIA-6463
PP_007ESWE
Outlier, +ve
BIA-6466
PP_007ESXC
Outlier, +ve
BIA-6763
PP_007EY8K
Outlier, +ve
MG-0073
PP_007EVWB
Outlier, +ve
MG-0624
PP_007EW7P
Outlier, +ve
MG-0705
PP_007EWDB
Outlier, +ve
MG-0738
PP_007EWG5
Outlier, +ve
MG-0811
PP_007EWPQ
Outlier, +ve
NIZ-146
PP_007C6Y0
Outlier, -ve
Genomes are excluded due to an excess of T->C mutations in short spans characteristic of putative ADAR editing, or because they lie outside two stderr above the regression line (+ve) or below (-ve).