
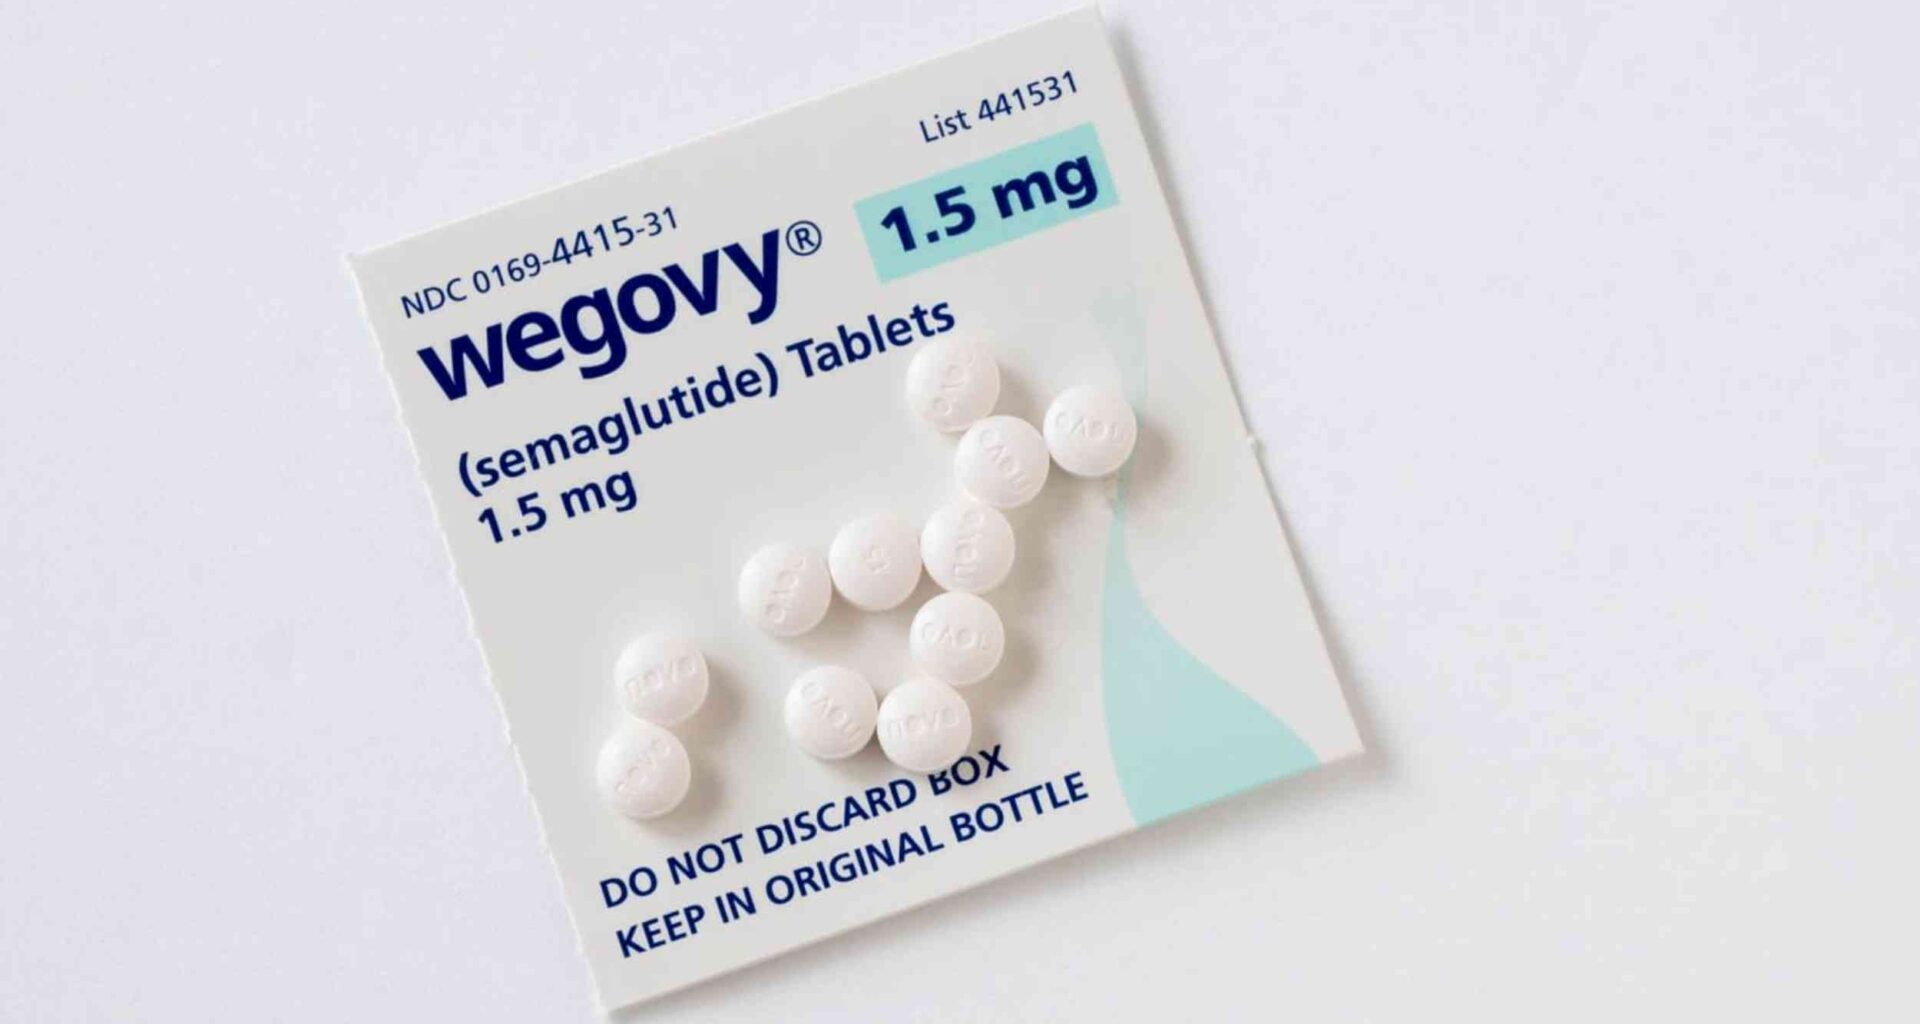
A new study has found that common DNA changes can help determine how much weight people lose on widely used weight-loss drugs like Ozempic or Mounjaro.
The finding points to the drugs’ own target receptors, recasting uneven results and stomach side effects as part of the same biological story.
Why results differ

In a survey that drew responses from nearly 28,000 people taking these drugs, weight loss ranged from modest to dramatic.
Working from those reports, scientists at the 23andMe Research Institute traced part of that divide to a receptor gene tied directly to the drugs’ action.
Each copy of the key variant linked to about 1.7 extra pounds lost, a modest gain that still marked a clear genetic edge.
That edge does not explain most of the difference between patients, which is why the rest of the picture still needs to be filled in.
Where genes act
That receptor sits on cells that help control appetite, so a tiny DNA change can alter the message these drugs deliver.
The team found the signal in GLP1R, the gene that controls how the body responds to these drugs, rather than in a distant helper pathway.
Because that DNA change alters the receptor’s protein directly, it is easier to connect the variant to the drug’s effect.
Researchers think the altered protein may help more receptors reach the cell surface, which could strengthen the drug signal.
Side effects overlap
One clue came from the same stretch of DNA when the team looked at people reporting nausea or vomiting.
Signals near GLP1R tracked with those stomach side effects, which fits the idea that stronger receptor activity can cut both ways.
In the dataset, people with more nausea or vomiting also tended to show greater weight loss on these drugs.
That link does not mean feeling sicker is good, but it hints that benefit and burden can share biology.
A second receptor
Unlike semaglutide, a drug that mimics a natural hormone to reduce appetite, tirzepatide also activates a second hormone pathway that can change how the stomach and brain react.
In that extra pathway, a variant in GIPR – a gene that helps cells respond to a gut hormone linked to digestion – raised vomiting risk only in tirzepatide. This drug targets two hormone systems instead of one.
People carrying high-risk versions at both receptor genes had about 15 times the odds of vomiting on tirzepatide.
That drug-specific pattern matters because it separates a semaglutide story from a tirzepatide story instead of lumping them together.
Limits of genetic influence
Genes were not the biggest driver, and the analysis is careful about that point throughout.
Sex, drug choice, dose, time on treatment, and diabetes status explained more of the weight-loss difference than genetics did.
Among participants, women tended to lose more weight, and people with type 2 diabetes tended to lose less.
That balance keeps the finding useful and honest, since DNA explains part of the story rather than the whole thing.
Estimating treatment response
After combining genes with medical history, the group could sort people into meaningfully different response groups.
That model explained about one-quarter of the difference in weight loss from person to person, with most power coming from non-genetic inputs.
In a public blog, the team said projected one-year outcomes ran from about 6% to 20% weight loss.
Nausea or vomiting risk in the same tool stretched from 5% to 78%, showing how wide the gap can be.
Records backed surveys
Survey answers made the study possible, but medical records gave the team a tougher test.
When 195 people had both sources, the two measures moved together, although self-reported weight loss still ran higher.
A separate check in the NIH’s All of Us program found the main efficacy signal again, which strengthened confidence in the result.
That cross-check also exposed a limit, because people remember treatment differently and health records often miss care received elsewhere.
Growing use of these drugs
Use of GLP-1 receptor agonists, drugs that copy gut signals and curb appetite, has spread fast across the United States.
One national poll found about one in eight U.S. adults had already tried one of these medications.
In a pivotal semaglutide trial, adults with overweight or obesity lost about 14.9% of body weight after 68 weeks.
A large tirzepatide trial pushed average loss even higher, which explains why response differences now matter so much.
Limits of current use
Clinicians still cannot use a cheek swab to pick the perfect drug, dose, or pace for any one patient.
Even so, the study sketches precision medicine, treatment tailored to a person’s biology, in a field still dominated by trial and error.
“Identifying these variants in the GLP1R and GIPR genes provides an important new insight into why these medications impact people in distinct ways,” said Dr. Adam Auton, Vice President of Human Genetics at 23andMe Research Institute.
For now, the most sensible next step is larger and more diverse testing that shows when genetics changes an actual prescription.
Next steps in research
What emerges is a sharper picture of why the same popular drugs can feel powerful, disappointing, or intolerable across patients.
As datasets expand beyond mostly female and mostly European samples, the promise will depend on showing that these signals can guide better choices in clinics.
The study is published in Nature.
—–
Like what you read? Subscribe to our newsletter for engaging articles, exclusive content, and the latest updates.
Check us out on EarthSnap, a free app brought to you by Eric Ralls and Earth.com.
—–